
UNITED STATES
SECURITIES AND EXCHANGE COMMISSION
WASHINGTON, D.C. 20549
FORM
CURRENT REPORT
Pursuant to Section 13 or 15(d)
of the Securities Exchange Act of 1934
Date of Report (Date of earliest event reported):
(Exact name of Registrant as Specified in Its Charter)
| (State or Other Jurisdiction of Incorporation) |
(Commission File Number) |
(IRS Employer Identification No.) |
| (Address of Principal Executive Offices) | (Zip Code) |
Registrant’s Telephone Number, Including Area Code:
N/A
(Former Name or Former Address, if Changed Since Last Report)
Check the appropriate box below if the Form 8-K filing is intended to simultaneously satisfy the filing obligation of the registrant under any of the following provisions (see General Instruction A.2. below):
| Written communications pursuant to Rule 425 under the Securities Act (17 CFR 230.425) |
| Soliciting material pursuant to Rule 14a-12 under the Exchange Act (17 CFR 240.14a-12) |
| Pre-commencement communications pursuant to Rule 14d-2(b) under the Exchange Act (17 CFR 240.14d-2(b)) |
| Pre-commencement communications pursuant to Rule 13e-4(c) under the Exchange Act (17 CFR 240.13e-4(c)) |
Securities registered pursuant to Section 12(b) of the Act:
| Title of each class |
Trading |
Name of each exchange on which registered | ||
Indicate by check mark whether the registrant is an emerging growth company as defined in Rule 405 of the Securities Act of 1933 (§ 230.405 of this chapter) or Rule 12b-2 of the Securities Exchange Act of 1934 (§ 240.12b-2 of this chapter).
Emerging growth company
If an emerging growth company, indicate by check mark if the registrant has elected not to use the extended transition period for complying with any new or revised financial accounting standards provided pursuant to Section 13(a) of the Exchange Act. ☐
| Item 7.01 | Regulation FD Disclosure. |
On October 19, 2026, Disc Medicine, Inc. (the “Company”) issued a press release titled “Disc Medicine Announces Success on All Primary and Secondary Endpoints in the Pivotal Phase 3 APOLLO Trial of Bitopertin in Adults and Adolescents with Erythropoietic Protoporphyria (EPP).” A copy of the press release is attached as Exhibit 99.1 to this Current Report on Form 8-K.
The information contained in Item 7.01 of this Current Report on Form 8-K (including Exhibit 99.1 attached hereto) is intended to be furnished and shall not be deemed “filed” for purposes of Section 18 of the Securities Exchange Act of 1934 (the “Exchange Act”), or otherwise subject to the liabilities of that section, nor shall it be deemed incorporated by reference in any filing under the Securities Act of 1933, as amended (the “Securities Act”) or the Exchange Act, except as expressly provided by specific reference in such filing. The Company undertakes no obligation to update, supplement or amend the materials attached hereto as Exhibit 99.1.
| Item 8.01 | Other Events. |
Webcast Presentation
On October 19, 2026, the Company will host a webcast to discuss topline results from the APOLLO Phase 3 trial of bitopertin in erythropoietic protoporphyria (“EPP”). A copy of the presentation from the webcast is filed as Exhibit 99.2 to this Current Report on Form 8-K and incorporated herein by reference. The presentation will also be available in the investor relations section of the Company’s website at https://ir.discmedicine.com. Information contained on the Company’s website is not incorporated by reference into this Current Report on Form 8-K, and you should not consider any information on, or that can be accessed from, the Company’s website as part of this Current Report on Form 8-K.
Bitopertin: Phase 3 APOLLO Topline Data Results
On October 19, 2026, the Company announced positive topline results from the APOLLO Phase 3 trial of bitopertin in EPP, including X-linked protoporphyria (“XLP”). The trial met all its primary and secondary endpoints.
APOLLO is a randomized, double-blind pivotal Phase 3 trial evaluating the safety and efficacy of bitopertin versus placebo in adults and adolescents aged 12 or older with EPP or XLP. The trial enrolled 183 patients across the United States, Canada, Europe, and Australia, who were stratified by baseline light tolerance and geography and randomized 1:1 to receive 60 mg oral bitopertin or placebo once daily for 6 months.
Summary of topline results:
| • | Bitopertin achieved statistical significance on both co-primary endpoints vs. placebo: |
| • | Reduction in whole-blood metal-free protoporphyrin IX (“PPIX”) from baseline (-41.4% vs. placebo, p<0.0001) |
| • | Increase in average monthly total time in light without pain during month 6 (+12.2 hours vs. placebo, p=0.0010) |
| • | Bitopertin achieved statistical significance on all secondary endpoints vs. placebo, including: |
| • | Reduction in incidence rate of phototoxic reactions over the 6-month treatment period vs. placebo (p<0.0001) |
| • | Increase in cumulative total time in light without pain over the 6-month treatment period vs. placebo (p<0.0001) |
| • | Increase in change from baseline in average daily sunlight exposure time to prodrome vs. placebo (p=0.0077, adults only) |
| • | Bitopertin demonstrated additional quality of life benefits vs. placebo, including improved Patient Global Impression of Change (“PGIC”) score (p<0.0001) and Patient Global Impression of Severity (“PGIS”) score (p<0.0001) |
| • | Bitopertin was generally well-tolerated. Consistent with prior studies, dizziness was the most commonly reported treatment emergent adverse event (“TEAE”) in the bitopertin group (50%) and was mild or moderate and generally transient. There were no TEAEs above Grade 3. |
The APOLLO clinical trial adds to an extensive clinical data package supporting bitopertin’s potential in EPP. Based on these results, the Company plans to resubmit a New Drug Application (“NDA”) to the U.S. Food and Drug Administration (“FDA”) by the end of 2026, with an FDA decision anticipated by mid-2027.
This Current Report on Form 8-K contains forward-looking statements within the meaning of Section 27A of the Securities Act, and Section 21E of the Exchange Act. Any statements about the Company’s expectations, beliefs, plans, objectives, assumptions or future events or performance are not historical facts and may be forward-looking. These statements are often, but are not always, made through the use of words or phrases such as “may,” “will,” “could,” “should,” “expects,” “intends,” “plans,” “anticipates,” “believes,” “estimates,” “predicts,” “projects,” “seeks,” “endeavor,” “potential,” “continue,” and similar expressions, or the negative of these terms, or similar expressions. These forward-looking statements include statements about the Company’s expectations with respect to the next stages of its development programs for bitopertin, anticipated engagement with regulators with respect to bitopertin, including the timing of an NDA resubmission and an FDA decision; and the potential therapeutic benefits of bitopertin as a treatment for EPP, if approved. Accordingly, these statements involve estimates, assumptions, risks and uncertainties which could cause actual results to differ materially from those expressed in them, including the uncertainties related to the adequacy of the Company’s capital to support its future operations and its ability to successfully initiate and complete clinical trials; the nature, strategy and focus of the Company; the difficulty in predicting the time and cost of development of the Company’s product candidates; the Company’s plans to research, develop and commercialize its current and future product candidates; the timing of initiation of the Company’s planned preclinical studies and clinical trials; the timing of the availability of data from the Company’s clinical trials; the Company’s ability to identify additional product candidates with significant commercial potential and to expand its pipeline in hematological diseases; the timing and anticipated results of the Company’s preclinical studies and clinical trials and the risk that the results of the Company’s preclinical studies and clinical trials may not be predictive of future results in connection with future studies or clinical trials and may not support further development and marketing approval; the content and timing of decisions made by the FDA and other regulatory authorities. The Company’s forward-looking statements also involve assumptions that, if they prove incorrect, would cause its results to differ materially from those expressed or implied by such forward-looking statements. These and other risks concerning the Company’s business are described in additional detail in the Company’s Quarterly Report on Form 10-Q for the quarter ended June 30, 2026 and other documents filed by the Company from time to time with the Securities and Exchange Commission. The Company is under no obligation to, and expressly disclaims any such obligation to, update or alter its forward-looking statements, whether as a result of new information, future events or otherwise.
| Item 9.01. | Exhibits. |
(d) Exhibits
| Exhibit No. |
Description | |
| 99.1 | Press release issued by Disc Medicine, Inc. on October 19, 2026, furnished herewith. | |
| 99.2 | Disc Medicine, Inc. Investor Presentation, filed herewith. | |
| 104 | Cover Page Interactive Data File (embedded within the Inline XBRL document) | |
SIGNATURES
Pursuant to the requirements of the Securities Exchange Act of 1934, the registrant has duly caused this report to be signed on its behalf by the undersigned hereunto duly authorized.
| DISC MEDICINE, INC. | ||||||
| Date: October 19, 2026 | By: | /s/ John Quisel | ||||
| Name: | John Quisel, J.D., Ph.D. | |||||
| Title: | Chief Executive Officer | |||||
Exhibit 99.1

Disc Medicine Announces Success on All Primary and Secondary Endpoints in the Pivotal Phase 3 APOLLO Trial of Bitopertin in Adults and Adolescents with Erythropoietic Protoporphyria (EPP)
| • | Positive APOLLO trial topline results demonstrated statistically significant and clinically meaningful benefit across all study endpoints |
| • | Successfully met co-primary endpoints of reduction in protoporphyrin IX (PPIX) and increased total time in light |
| • | All secondary endpoint results were also positive and statistically significant, including reductions in phototoxic reactions and improvements on multiple measures of light tolerance |
| • | Exploratory endpoints of quality-of-life improvement were also statistically significant |
| • | Bitopertin was generally well-tolerated with no new safety signals observed in APOLLO |
| • | Disc plans to resubmit an NDA to FDA by end of 2026, with an FDA decision anticipated by mid-2027 |
| • | Disc to discuss topline results in a corporate webcast on October 19, 2026 at 8:00am ET |
WATERTOWN, Mass., October 19, 2026 – Disc Medicine, Inc. (NASDAQ:IRON), a clinical stage biopharmaceutical company focused on the discovery, development, and commercialization of novel treatments for patients suffering from serious hematologic diseases, today announced topline results from the APOLLO Phase 3 trial of bitopertin in erythropoietic protoporphyria (EPP), including X-linked protoporphyria (XLP). The trial met all its primary and secondary endpoints.
“Today represents a potential breakthrough in the science and treatment of EPP,” said John Quisel, J.D., Ph.D., President and Chief Executive Officer of Disc Medicine. “We could not have hoped for a better outcome, and we are grateful to the patients, caregivers, and physicians who have partnered with us throughout the clinical development of bitopertin. We look forward to engaging with regulators with the goal of bringing an important, innovative medicine to this community as efficiently as possible.”
“This is the first time a potential treatment for EPP has shown robust evidence of whole blood PPIX reduction alongside unequivocal improvement on important measures of disease severity: increased time in light, reduced phototoxic reactions, and improved Patient Reported Outcome scores,” said Herbert L. Bonkovsky, M.D., Director of Gastroenterology & Internal Medicine, Professor Emeritus of Medicine at Wake Forest University School of Medicine, and a Principal Investigator of APOLLO.
“These results are compelling evidence of the clinical benefit of a mechanism aimed at reducing the production of PPIX, the fundamental cause of disease,” added Will Savage, M.D., Ph.D., Chief Medical Officer of Disc Medicine. “It has been an incredible journey from establishing the original hypothesis of targeting heme synthesis in cellular models to seeing that biology translate into the clear and meaningful clinical effects from APOLLO. We plan to share more detailed data with additional insights from APOLLO at a future medical conference.”
APOLLO is a randomized, double-blind pivotal Phase 3 trial evaluating the safety and efficacy of bitopertin versus placebo in adults and adolescents aged 12 or older with EPP or XLP. The trial enrolled 183 patients across the United States, Canada, Europe, and Australia, who were stratified by baseline light tolerance and geography and randomized 1:1 to receive 60 mg oral bitopertin or placebo once daily for 6 months.
Summary of topline results:
| • | Bitopertin achieved statistical significance on both co-primary endpoints vs. placebo: |
| • | Reduction in whole-blood metal-free PPIX from baseline (-41.4% vs. placebo, p<0.0001) |
| • | Increase in average monthly total time in light without pain during month 6 (+12.2 hours vs. placebo, p=0.0010) |
| • | Bitopertin achieved statistical significance on all secondary endpoints vs. placebo, including: |
| • | Reduction in incidence rate of phototoxic reactions over the 6-month treatment period vs. placebo (p<0.0001) |
| • | Increase in cumulative total time in light without pain over the 6-month treatment period vs. placebo (p<0.0001) |
| • | Increase in change from baseline in average daily sunlight exposure time to prodrome vs. placebo (p=0.0077, adults only) |
| • | Bitopertin demonstrated additional quality of life benefits vs. placebo, including improved Patient Global Impression of Change (PGIC) score (p<0.0001) and Patient Global Impression of Severity (PGIS) score (p<0.0001) |
| • | Bitopertin was generally well-tolerated. Consistent with prior studies, dizziness was the most commonly reported treatment emergent adverse event (TEAE) in the bitopertin group (50%) and was mild or moderate and generally transient. There were no TEAEs above Grade 3. |
The APOLLO study adds to an extensive clinical data package supporting bitopertin’s potential in EPP. Based on these results, Disc plans to resubmit a New Drug Application (NDA) to the U.S. FDA by the end of 2026, with an FDA decision anticipated by mid-2027.
Management will host a corporate webcast this morning, Monday, October 19 at 8:00am EST to discuss the APOLLO topline results and next steps. Please register for the event on the Events and Presentations page of Disc’s website (https://ir.discmedicine.com/).
About Bitopertin
Bitopertin is an investigational, clinical-stage, orally administered inhibitor of glycine transporter 1 (GlyT1) that is designed to modulate heme biosynthesis. GlyT1 is a membrane transporter expressed on developing red blood cells and is required to supply sufficient glycine for heme biosynthesis and support erythropoiesis. Disc is planning to develop bitopertin as a potential treatment for a range of hematologic diseases including erythropoietic porphyrias, where it has potential to be the first disease-modifying therapy. Bitopertin has been studied in multiple clinical trials in patients with EPP, including the Phase 2 open-label BEACON trial, the Phase 2 double-blind, placebo-controlled AURORA trial, the open-label extension HELIOS trial, and the APOLLO trial.
Bitopertin is an investigational agent and is not approved for use as a therapy in any jurisdiction worldwide. Disc obtained global rights to bitopertin under a license agreement from Roche in May 2021.
About EPP
Erythropoietic protoporphyria (EPP), including X-linked Protoporphyria (XLP), is a rare, debilitating and potentially life-threatening disease caused by mutations that affect heme biosynthesis, resulting in the accumulation of a toxic, photoactive intermediate called protoporphyrin IX (PPIX). This causes severe reactions when patients are exposed to sunlight, characterized by excruciating pain, edema, burning sensations and potential blistering and disfigurement. PPIX also accumulates in the hepatobiliary system and can result in complications including gallstones, cholestasis, and liver damage in 20-30% of patients and in extreme cases liver failure. Current standard of care involves extreme measures to avoid sunlight, including restricting outdoor activities to nighttime, use of protective clothing and opaque shields, and pain management. This has a significant impact on the psychosocial development, quality of life, and daily activities of patients, particularly in young children and families. There is currently no cure for EPP and only one FDA-approved therapy, a surgically implanted synthetic hormone designed to stimulate melanin production called Scenesse® (afamelanotide).
About Disc Medicine
Disc Medicine is a clinical-stage biopharmaceutical company committed to discovering, developing, and commercializing novel treatments for patients who suffer from serious hematologic diseases. We are building a portfolio of innovative, potentially first-in-class therapeutic candidates that aim to address a wide spectrum of hematologic diseases by targeting fundamental biological pathways of red blood cell biology, specifically heme biosynthesis and iron homeostasis. For more information, please visit www.discmedicine.com.
Disc Cautionary Statement Regarding Forward-Looking Statements
This press release contains “forward-looking statements” within the meaning of the Private Securities Litigation Reform Act of 1995, including, but not limited to, express or implied statements regarding Disc’s expectations with respect to: the next stages of its development of bitopertin; anticipated engagement with regulators with respect to bitopertin, including the timing of an NDA resubmission and an FDA decision; and the potential therapeutic benefits of bitopertin as a treatment for EPP, if approved. The use of words such as, but not limited to, “believe,” “expect,” “estimate,” “project,” “intend,” “future,” “potential,” “continue,” “may,” “might,” “plan,” “will,” “should,” “seek,” “anticipate,” or “could” or the negative of these terms and other similar words or expressions that are intended to identify forward-looking statements. Forward-looking statements are neither historical facts nor assurances of future performance. Instead, they are based on Disc’s current beliefs, expectations and assumptions regarding the future of Disc’s business, future plans and strategies, clinical results and other future conditions. New risks and uncertainties may emerge from time to time, and it is not possible to predict all risks and uncertainties. No representations or warranties (expressed or implied) are made about the accuracy of any such forward-looking statements.
Disc may not actually achieve the plans, intentions or expectations disclosed in these forward-looking statements, and investors should not place undue reliance on these forward-looking statements. Actual results or events could differ materially from the plans, intentions and expectations disclosed in the forward-looking statements as a result of a number of material risks and uncertainties including but not limited to: the adequacy of Disc’s capital to support its future operations and its ability to successfully initiate and complete clinical trials; the nature,
strategy and focus of Disc; the difficulty in predicting the time and cost of development of Disc’s product candidates; Disc’s plans to research, develop and commercialize its current and future product candidates; the timing of initiation of Disc’s planned preclinical studies and clinical trials; the timing of the availability of data from Disc’s clinical trials; Disc’s ability to identify additional product candidates with significant commercial potential and to expand its pipeline in hematological diseases; the timing and anticipated results of Disc’s preclinical studies and clinical trials and the risk that the results of Disc’s preclinical studies and clinical trials may not be predictive of future results in connection with future studies or clinical trials and may not support further development and marketing approval; the content and timing of decisions made by the FDA and other regulatory authorities; and the other risks and uncertainties described in Disc’s filings with the Securities and Exchange Commission, including in the “Risk Factors” section of Disc’s Annual Report on Form 10-K for the year ended December 31, 2025, and in subsequent Quarterly Reports on Form 10-Q. Any forward-looking statement speaks only as of the date on which it was made. None of Disc, nor its affiliates, advisors or representatives, undertake any obligation to publicly update or revise any forward-looking statement, whether as result of new information, future events or otherwise, except as required by law.
Media Contact
Peg Rusconi
Deerfield Group
peg.rusconi@deerfieldgroup.com
Investor Relations Contact
Kevin Lui
Precision AQ
kevin.lui@precisionaq.com

APOLLO Topline Results October 19, 2026 Exhibit 99.2

Disclaimer and FLS This presentation contains “forward-looking statements” within the meaning of the Private Securities Litigation Reform Act of 1995, including, but not limited to, express or implied statements regarding Disc’s expectations with respect to its preclinical studies, clinical trials and research and development programs, in particular with respect to bitopertin, selcodebart (DISC-0974) and DISC-3405, and any developments or results in connection therewith; projected timelines for the initiation and completion of its clinical trials, anticipated timing of release of data, and other clinical and commercial readiness activities; the registrational pathway for bitopertin, including the projected timeline for an NDA resubmission and the timing of an FDA decision; anticipated discussions with regulatory agencies; Disc’s expectations with respect to the potential launch and commercialization of bitopertin, if approved; the potential therapeutic benefits of bitopertin as a treatment for EPP, if approved; the market and potential opportunities for bitopertin, selcodebart and DISC-3405; the potential of Disc’s development programs in new indications; and the time period over which Disc’s capital resources will be sufficient to fund its anticipated operations. The use of words such as, but not limited to, “believe,” “expect,” “estimate,” “project,” “intend,” “future,” “potential,” “continue,” “may,” “might,” “plan,” “will,” “should,” “seek,” “anticipate,” or “could” or the negative of these terms and other similar words or expressions that are intended to identify forward-looking statements. Forward-looking statements are neither historical facts nor assurances of future performance. Instead, they are based on Disc’s current beliefs, expectations and assumptions regarding the future of Disc’s business, future plans and strategies, clinical results and other future conditions. New risks and uncertainties may emerge from time to time, and it is not possible to predict all risks and uncertainties. No representations or warranties (expressed or implied) are made about the accuracy of any such forward-looking statements. Disc may not actually achieve the plans, intentions or expectations disclosed in these forward-looking statements, and investors should not place undue reliance on these forward-looking statements. Actual results or events could differ materially from the plans, intentions and expectations disclosed in the forward-looking statements as a result of a number of material risks and uncertainties including but not limited to: the adequacy of Disc’s capital to support its future operations and its ability to successfully initiate and complete clinical trials; the nature, strategy and focus of Disc; the difficulty in predicting the time and cost of development of Disc’s product candidates; Disc’s plans to research, develop and commercialize its current and future product candidates; the timing of initiation of Disc’s planned preclinical studies and clinical trials; the timing of the availability of data from Disc’s clinical trials; Disc’s ability to identify additional product candidates with significant commercial potential and to expand its pipeline in hematological diseases; the timing and anticipated results of Disc’s preclinical studies and clinical trials and the risk that the results of Disc’s preclinical studies and clinical trials may not be predictive of future results in connection with future studies or clinical trials and may not support further development and marketing approval; the content and timing of decisions made by the FDA and other regulatory authorities; and the other risks and uncertainties described in Disc’s filings with the Securities and Exchange Commission, including in the “Risk Factors” section of Disc’s Annual Report on Form 10-K for the year ended December 31, 2025, and in subsequent Quarterly Reports on Form 10-Q. Any forward-looking statement speaks only as of the date on which it was made. None of Disc, nor its affiliates, advisors or representatives, undertake any obligation to publicly update or revise any forward-looking statement, whether as result of new information, future events or otherwise, except as required by law.

Bitopertin, selcodebart, and DISC-3405 are investigational agents and are not approved for use as therapies in any jurisdiction worldwide

Opening Remarks & Thank You
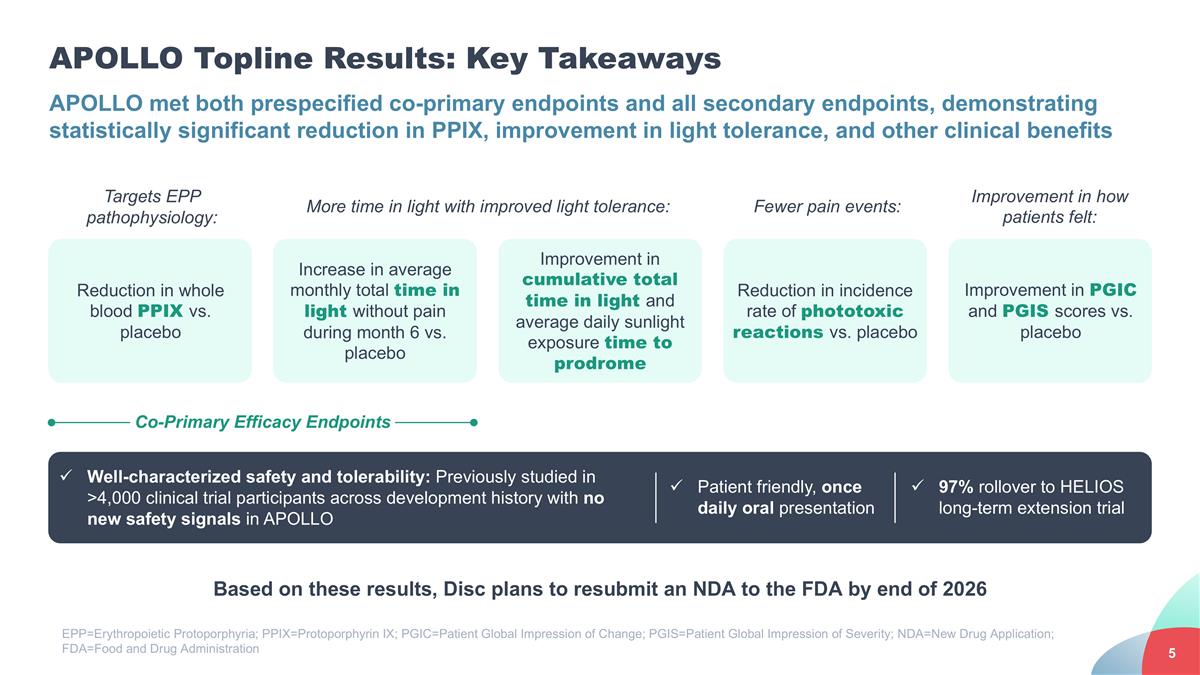
APOLLO Topline Results: Key Takeaways APOLLO met both prespecified co-primary endpoints and all secondary endpoints, demonstrating statistically significant reduction in PPIX, improvement in light tolerance, and other clinical benefits Reduction in incidence rate of phototoxic reactions vs. placebo Increase in average monthly total time in light without pain during month 6 vs. placebo Improvement in cumulative total time in light and average daily sunlight exposure time to prodrome Based on these results, Disc plans to resubmit an NDA to the FDA by end of 2026 Co-Primary Efficacy Endpoints Targets EPP pathophysiology: More time in light with improved light tolerance: Well-characterized safety and tolerability: Previously studied in >4,000 clinical trial participants across development history with no new safety signals in APOLLO Patient friendly, once daily oral presentation 97% rollover to HELIOS long-term extension trial Fewer pain events: Reduction in whole blood PPIX vs. placebo Improvement in PGIC and PGIS scores vs. placebo Improvement in how patients felt: EPP=Erythropoietic Protoporphyria; PPIX=Protoporphyrin IX; PGIC=Patient Global Impression of Change; PGIS=Patient Global Impression of Severity; NDA=New Drug Application; FDA=Food and Drug Administration

Opening Remarks & EPP Overview John Quisel, JD, PhD, Chief Executive Officer APOLLO Topline Data Review Will Savage, MD, PhD, Chief Medical Officer EPP Market Opportunity Pamela Stephenson, Chief Commercial Officer Closing Remarks and Q&A Session John Quisel, JD, PhD, Chief Executive Officer Agenda

Erythropoietic Protoporphyria (EPP) Rare, debilitating and lifelong condition characterized by extreme pain and damage to the skin caused by light, as well as potential hepatobiliary complications and psychosocial impacts Genetic condition caused by defective heme biosynthesis – deficient enzyme ferrochelatase Lifelong and presents in early childhood Caused by accumulation of toxic metabolite PPIX X-Linked Protoporphyria (XLP), mechanistically similar disease, also PPIX-related Debilitating and potentially life-threatening Skin: severe, disabling pain attacks (days), edema, burning Hepatobiliary disease: gallstones, liver dysfunction or failure Psychosocial well-being (fear, anxiety) and development No cure or disease-modifying treatment Avoid sun / light, protective clothing, window tinting, Zn/Ti Oxide One FDA-approved agent, afamelanotide, a surgically-implanted tanning agent Sources: Deybach et al (2009) Orphanet Journal of Rare Diseases; American Porphyria Foundation; Dickey et al (2021) Genet. Med.; Trinity Life Sciences; Komodo Claims Data (2016-2022); Balwani et al, JAMA Dermatology, 2017 Healthy liver EPP liver
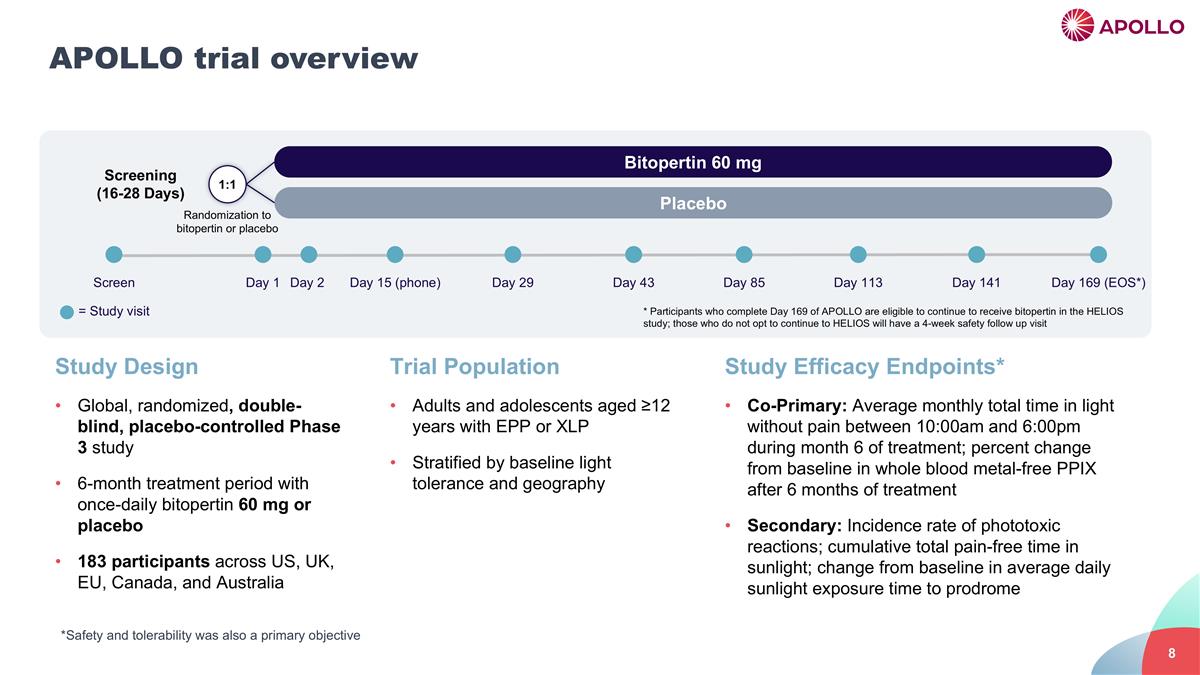
APOLLO trial overview Screen Day 1 Day 2 Day 15 (phone) Day 29 Day 43 Day 85 Day 141 Screening (16-28 Days) Day 169 (EOS*) 1:1 Placebo Bitopertin 60 mg Day 113 * Participants who complete Day 169 of APOLLO are eligible to continue to receive bitopertin in the HELIOS study; those who do not opt to continue to HELIOS will have a 4-week safety follow up visit Study Design Global, randomized, double-blind, placebo-controlled Phase 3 study 6-month treatment period with once-daily bitopertin 60 mg or placebo 183 participants across US, UK, EU, Canada, and Australia Study Efficacy Endpoints* Co-Primary: Average monthly total time in light without pain between 10:00am and 6:00pm during month 6 of treatment; percent change from baseline in whole blood metal-free PPIX after 6 months of treatment Secondary: Incidence rate of phototoxic reactions; cumulative total pain-free time in sunlight; change from baseline in average daily sunlight exposure time to prodrome Trial Population Adults and adolescents aged ≥12 years with EPP or XLP Stratified by baseline light tolerance and geography = Study visit *Safety and tolerability was also a primary objective Randomization to bitopertin or placebo
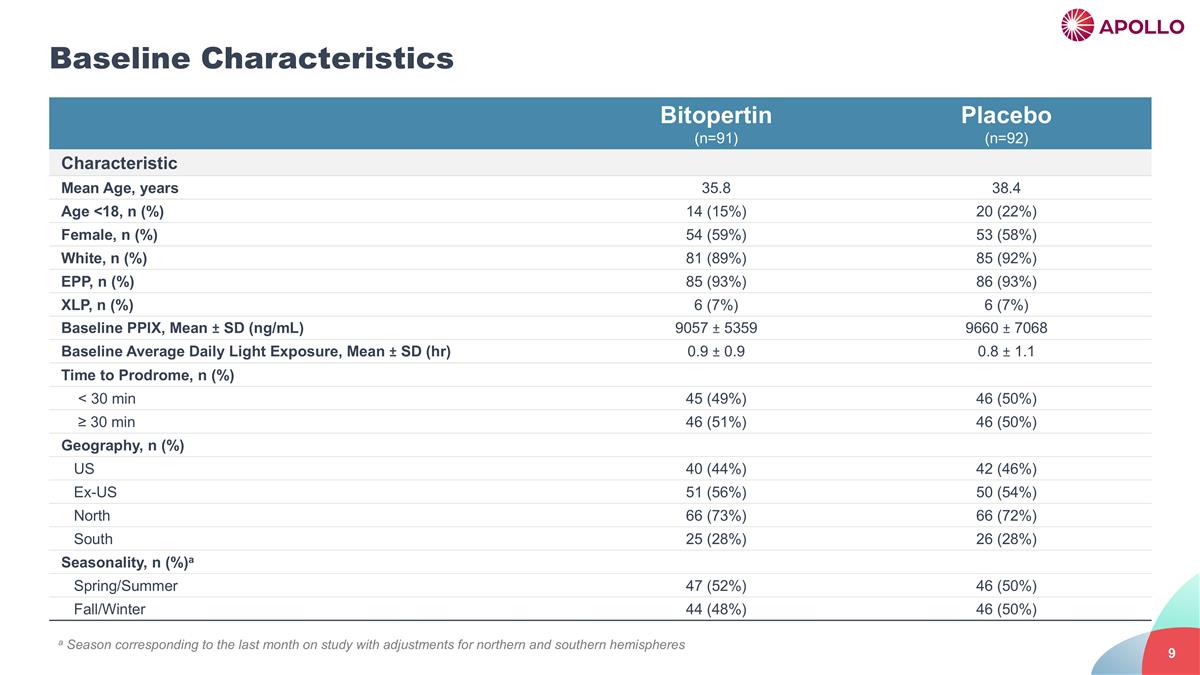
a Season corresponding to the last month on study with adjustments for northern and southern hemispheres Baseline Characteristics Bitopertin (n=91) Placebo (n=92) Characteristic Mean Age, years 35.8 38.4 Age <18, n (%) 14 (15%) 20 (22%) Female, n (%) 54 (59%) 53 (58%) White, n (%) 81 (89%) 85 (92%) EPP, n (%) 85 (93%) 86 (93%) XLP, n (%) 6 (7%) 6 (7%) Baseline PPIX, Mean ± SD (ng/mL) 9057 ± 5359 9660 ± 7068 Baseline Average Daily Light Exposure, Mean ± SD (hr) 0.9 ± 0.9 0.8 ± 1.1 Time to Prodrome, n (%) < 30 min 45 (49%) 46 (50%) ≥ 30 min 46 (51%) 46 (50%) Geography, n (%) US 40 (44%) 42 (46%) Ex-US 51 (56%) 50 (54%) North 66 (73%) 66 (72%) South 25 (28%) 26 (28%) Seasonality, n (%)a Spring/Summer 47 (52%) 46 (50%) Fall/Winter 44 (48%) 46 (50%) a Season corresponding to the last month on study with adjustments for northern and southern hemispheres
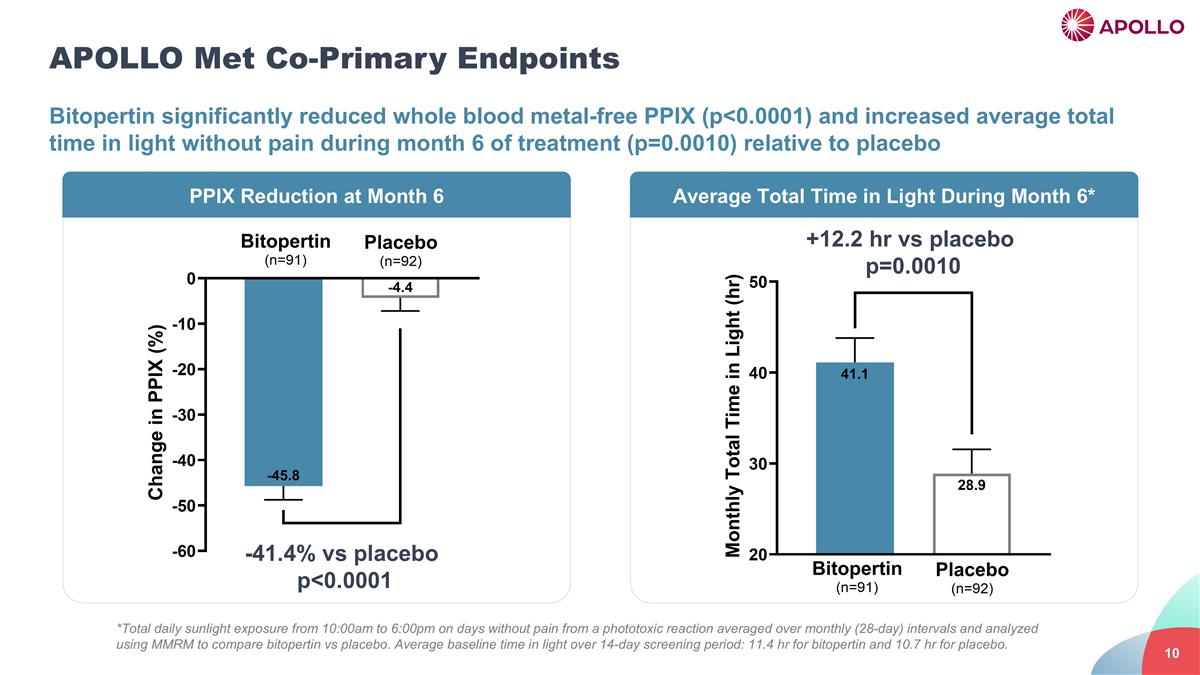
APOLLO Met Co-Primary Endpoints Bitopertin significantly reduced whole blood metal-free PPIX (p<0.0001) and increased average total time in light without pain during month 6 of treatment (p=0.0010) relative to placebo -41.4% vs placebo p<0.0001 PPIX Reduction at Month 6 Average Total Time in Light During Month 6* +12.2 hr vs placebo p=0.0010 *Total daily sunlight exposure from 10:00am to 6:00pm on days without pain from a phototoxic reaction averaged over monthly (28-day) intervals and analyzed using MMRM to compare bitopertin vs placebo. Average baseline time in light over 14-day screening period: 11.4 hr for bitopertin and 10.7 hr for placebo.
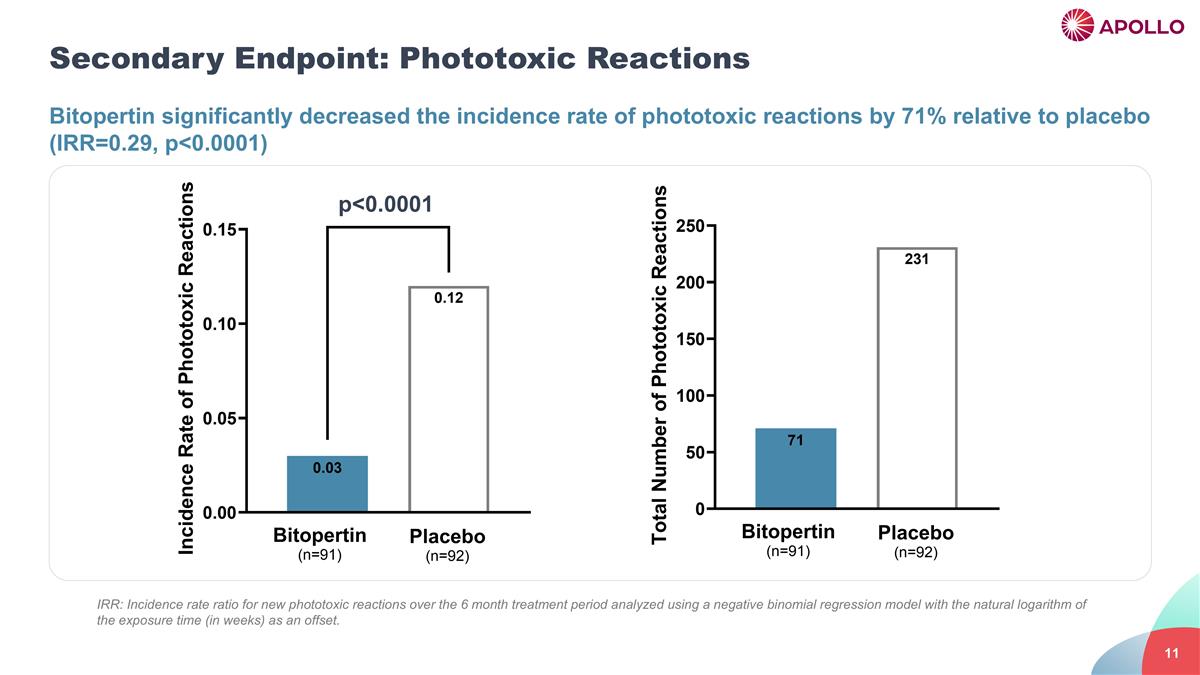
Secondary Endpoint: Phototoxic Reactions Bitopertin significantly decreased the incidence rate of phototoxic reactions by 71% relative to placebo (IRR=0.29, p<0.0001) p<0.0001 IRR: Incidence rate ratio for new phototoxic reactions over the 6 month treatment period analyzed using a negative binomial regression model with the natural logarithm of the exposure time (in weeks) as an offset.
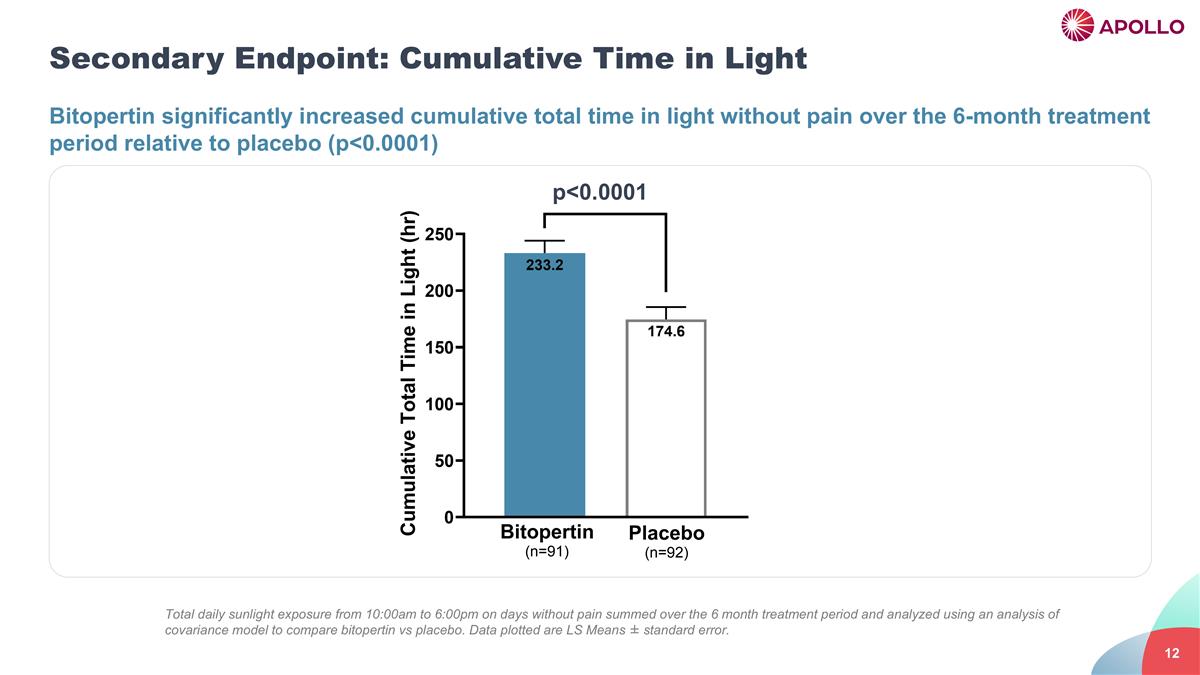
Secondary Endpoint: Cumulative Time in Light Bitopertin significantly increased cumulative total time in light without pain over the 6-month treatment period relative to placebo (p<0.0001) p<0.0001 Total daily sunlight exposure from 10:00am to 6:00pm on days without pain summed over the 6 month treatment period and analyzed using an analysis of covariance model to compare bitopertin vs placebo. Data plotted are LS Means ± standard error.
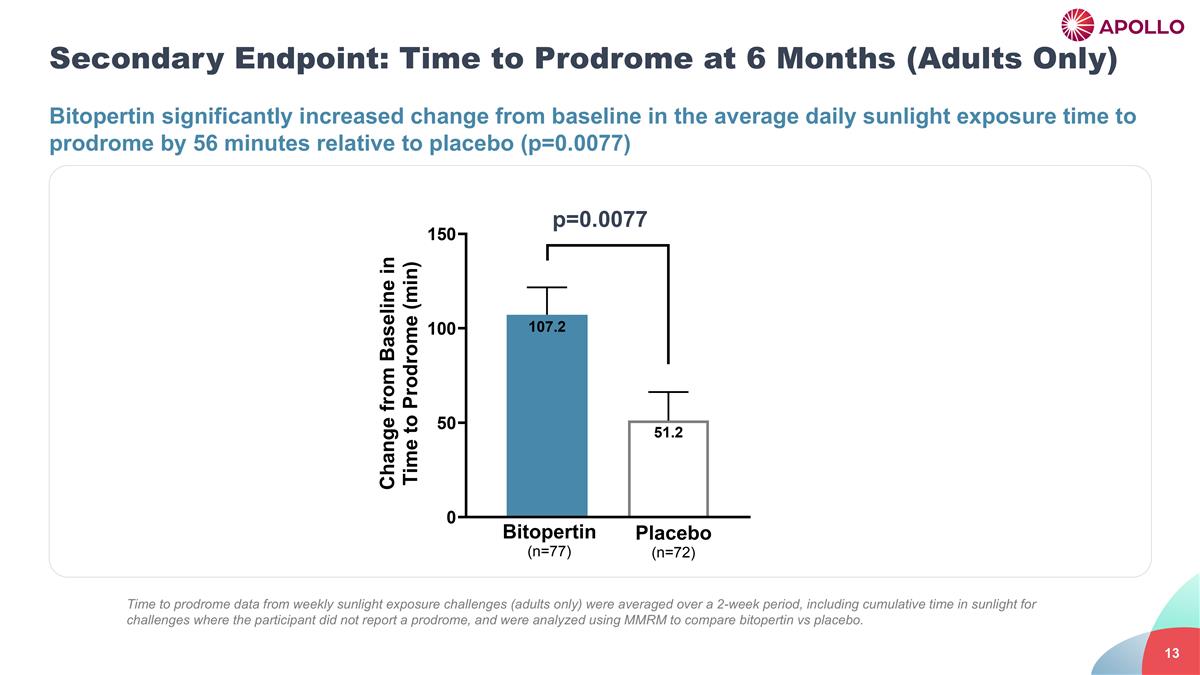
Secondary Endpoint: Time to Prodrome at 6 Months (Adults Only) Bitopertin significantly increased change from baseline in the average daily sunlight exposure time to prodrome by 56 minutes relative to placebo (p=0.0077) p=0.0077 Time to prodrome data from weekly sunlight exposure challenges (adults only) were averaged over a 2-week period, including cumulative time in sunlight for challenges where the participant did not report a prodrome, and were analyzed using MMRM to compare bitopertin vs placebo.
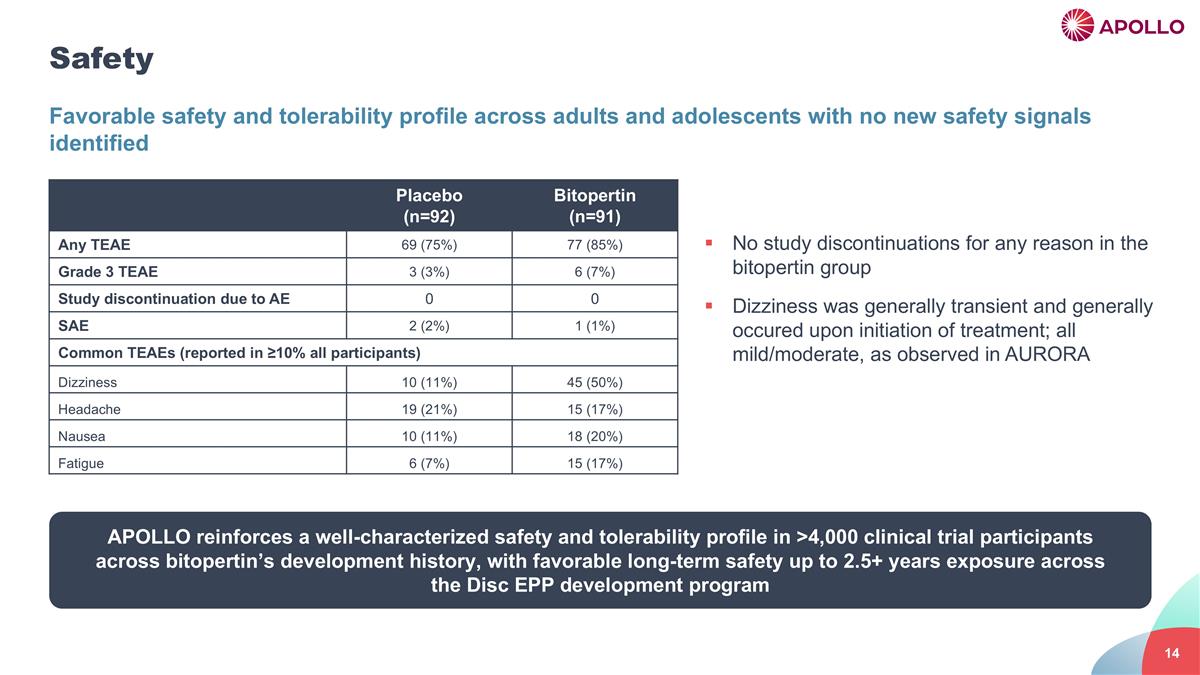
Safety Favorable safety and tolerability profile across adults and adolescents with no new safety signals identified APOLLO reinforces a well-characterized safety and tolerability profile in >4,000 clinical trial participants across bitopertin’s development history, with favorable long-term safety up to 2.5+ years exposure across the Disc EPP development program Placebo (n=92) Bitopertin (n=91) Any TEAE 69 (75%) 77 (85%) Grade 3 TEAE 3 (3%) 6 (7%) Study discontinuation due to AE 0 0 SAE 2 (2%) 1 (1%) Common TEAEs (reported in ≥10% all participants) Dizziness 10 (11%) 45 (50%) Headache 19 (21%) 15 (17%) Nausea 10 (11%) 18 (20%) Fatigue 6 (7%) 15 (17%) No study discontinuations for any reason in the bitopertin group Dizziness was generally transient and generally occured upon initiation of treatment; all mild/moderate, as observed in AURORA
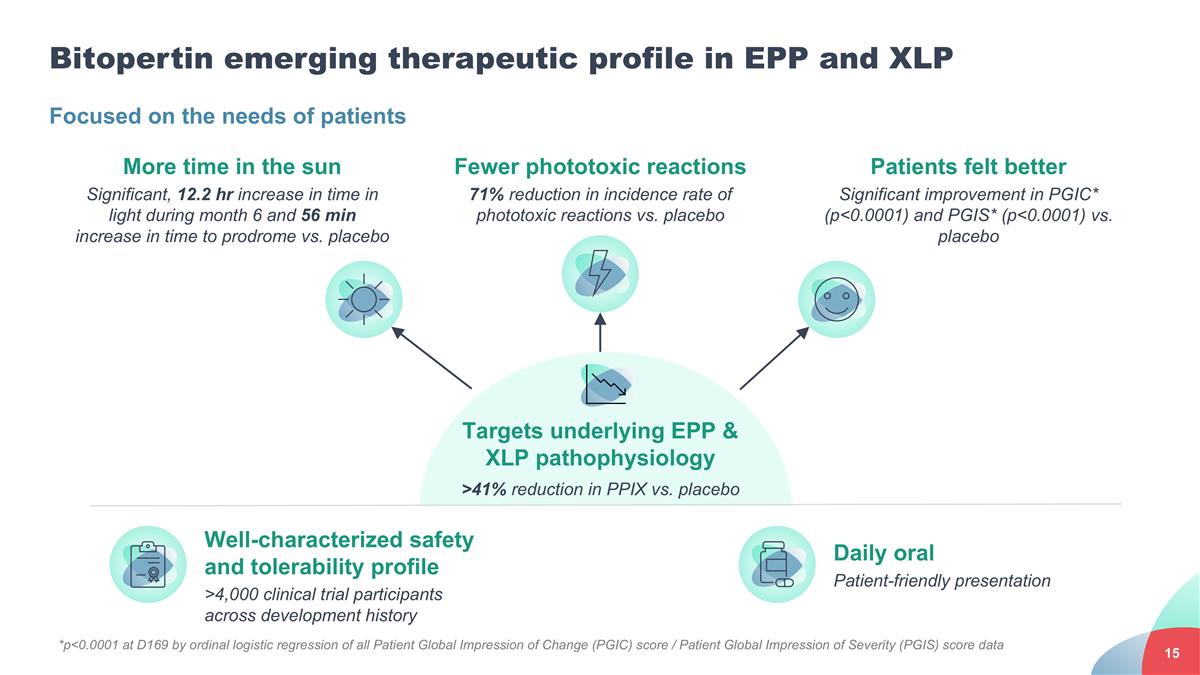
Targets underlying EPP & XLP pathophysiology >41% reduction in PPIX vs. placebo Bitopertin emerging therapeutic profile in EPP and XLP Focused on the needs of patients More time in the sun Significant, 12.2 hr increase in time in light during month 6 and 56 min increase in time to prodrome vs. placebo Fewer phototoxic reactions 71% reduction in incidence rate of phototoxic reactions vs. placebo Patients felt better Significant improvement in PGIC* (p<0.0001) and PGIS* (p<0.0001) vs. placebo Well-characterized safety and tolerability profile >4,000 clinical trial participants across development history Daily oral Patient-friendly presentation *p<0.0001 at D169 by ordinal logistic regression of all Patient Global Impression of Change (PGIC) score / Patient Global Impression of Severity (PGIS) score data

Opening Remarks & EPP Overview John Quisel, JD, PhD, Chief Executive Officer APOLLO Topline Data Review Will Savage, MD, PhD, Chief Medical Officer EPP Market Opportunity Pamela Stephenson, Chief Commercial Officer Closing Remarks and Q&A Session John Quisel, JD, PhD, Chief Executive Officer Agenda
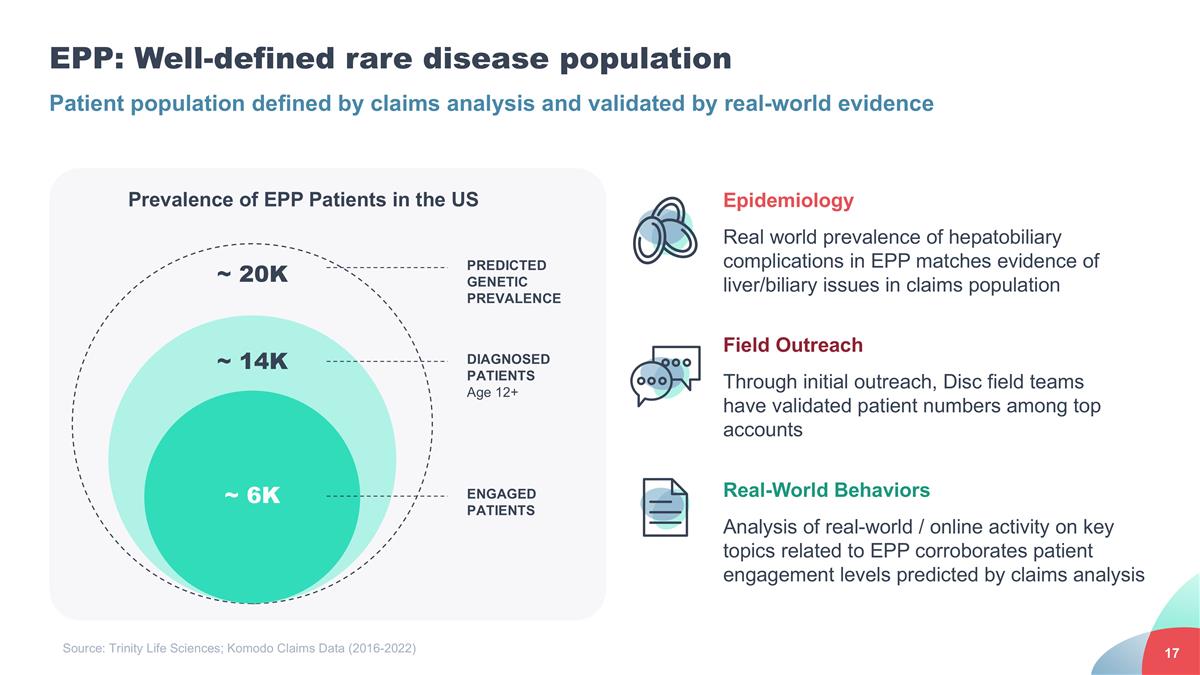
EPP: Well-defined rare disease population Epidemiology Real world prevalence of hepatobiliary complications in EPP matches evidence of liver/biliary issues in claims population Field Outreach Through initial outreach, Disc field teams have validated patient numbers among top accounts Real-World Behaviors Analysis of real-world / online activity on key topics related to EPP corroborates patient engagement levels predicted by claims analysis ~ 6K Prevalence of EPP Patients in the US ENGAGED PATIENTS ~ 14K ~ 20K DIAGNOSED PATIENTS Age 12+ PREDICTED GENETIC PREVALENCE Patient population defined by claims analysis and validated by real-world evidence Source: Trinity Life Sciences; Komodo Claims Data (2016-2022)

Account Profiling Disease State Education Patient Validation PPIX Testing Program Driving informed EPP awareness Identifying Regional Opinion Leaders (ROL) Engaged top porphyria centers Prioritized top community accounts Validated EPP opportunity at high-volume accounts Targeting launch Nov. 2026 Commercial priorities Focus on building EPP awareness, deepening market understanding, and addressing unmet needs

Opening Remarks & EPP Overview John Quisel, JD, PhD, Chief Executive Officer APOLLO Topline Data Review Will Savage, MD, PhD, Chief Medical Officer EPP Market Opportunity Pamela Stephenson, Chief Commercial Officer Closing Remarks and Q&A Session John Quisel, JD, PhD, Chief Executive Officer Agenda

Next steps for bitopertin in EPP NDA resubmission planned by end of 2026 based on APOLLO data; FDA decision anticipated by mid 2027 Planning to present detailed data with additional insights from APOLLO during an upcoming medical conference HELIOS open-label extension study ongoing for patients rolled over from BEACON, AURORA, and APOLLO Continuing site activation and enrollment in the Expanded Access Program (EAP) for bitopertin for eligible patients with EPP and XLP in the US and other select countries Continuing commercial readiness efforts with focus on disease education, account profiling, and patient validation
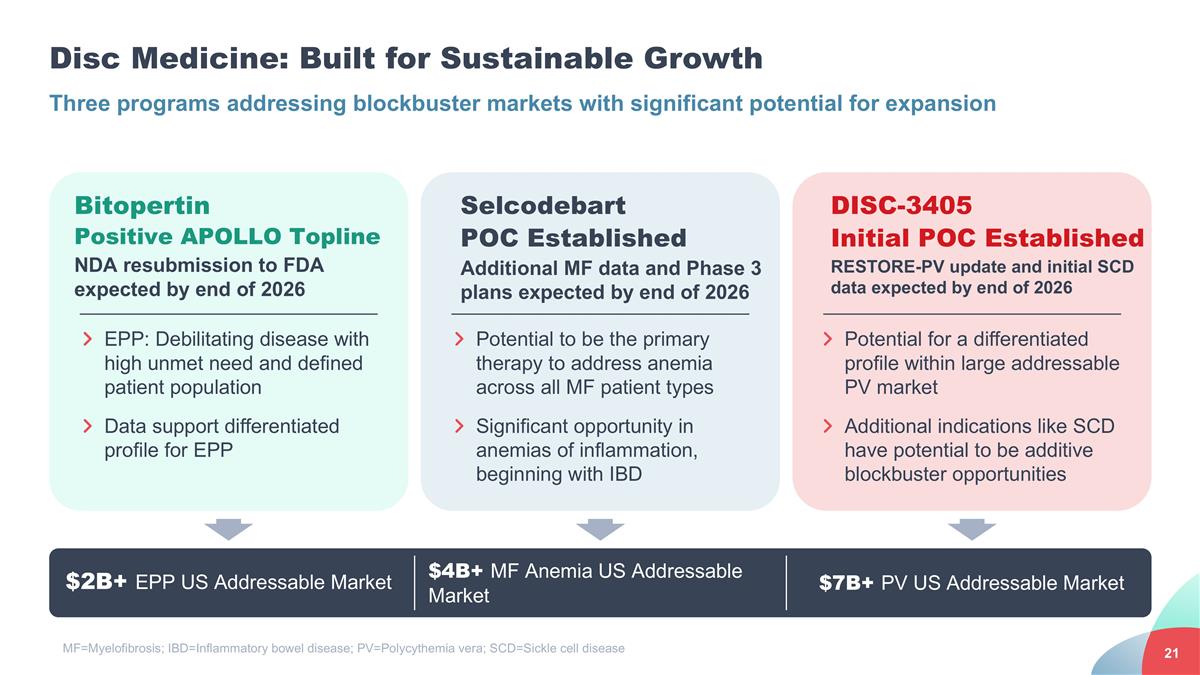
Disc Medicine: Built for Sustainable Growth Three programs addressing blockbuster markets with significant potential for expansion $2B+ EPP US Addressable Market $4B+ MF Anemia US Addressable Market Bitopertin Positive APOLLO Topline NDA resubmission to FDA expected by end of 2026 DISC-3405 Initial POC Established RESTORE-PV update and initial SCD data expected by end of 2026 EPP: Debilitating disease with high unmet need and defined patient population Data support differentiated profile for EPP Selcodebart POC Established Additional MF data and Phase 3 plans expected by end of 2026 Potential to be the primary therapy to address anemia across all MF patient types Significant opportunity in anemias of inflammation, beginning with IBD Potential for a differentiated profile within large addressable PV market Additional indications like SCD have potential to be additive blockbuster opportunities $7B+ PV US Addressable Market MF=Myelofibrosis; IBD=Inflammatory bowel disease; PV=Polycythemia vera; SCD=Sickle cell disease

Q&A We extend our deepest gratitude to the patients and families, investigators, and advocates whose commitment and partnership have been instrumental in raising awareness of EPP and advancing this program Brady Living with EPP Mary and Gia Mother caring for daughter with EPP